The treatment
What Radial Shockwave Therapy Is
Radial shockwave therapy (radial ESWT), one of the two forms of extracorporeal shockwave therapy, sends pressure waves through a broad, relatively shallow area of tissue. The waves start at the applicator and spread as they travel. We use it most often for fascia, muscle, and the surface of a tendon. We use it only when a comprehensive exam shows it suits the tissue.
How radial shockwave differs from focused
Radial pressure waves are strongest at the skin and weaken with depth. Focused shockwaves peak at a chosen depth for a small, deep target. Novo uses a Storz Orthopulse Ultra 100 for radial shockwave and a Storz Duolith SD1 T-Top Ultra for focused. See Radial vs. Focused Shockwave: What the Research Shows or the focused shockwave page.
Mechanism
How It Works
A radial device generates a pressure wave at the applicator. The wave spreads out and weakens as it travels, so its strongest effect is near the surface. That makes it suited to broad, shallow layers rather than a single deep point.
Proposed biologic effects overlap with focused shockwave: mechanotransduction, changes in local tissue and blood-vessel signaling, and effects on pain sensitivity. Experimental skeletal-muscle models have shown antifibrotic effects, but human evidence that radial shockwave remodels tissue is limited. Most clinical trials measure pain and function rather than tissue change.
Indications
When We May Use It
Radial shockwave may be considered when the examination identifies a broad, relatively superficial area that appears to be contributing to symptoms:
- muscle bellies and fascia, including post-injury or fibrotic tissue
- the surface of a tendon in selected tendinopathies
- the plantar fascia and other broad attachment regions
- myofascial areas in the neck, back and hip when the exam points there
Radial energy is used on scar and fibrosis as well as tendinopathy. It suits pain from a broad layer more than a single point. A condition appearing below does not mean radial shockwave is the right choice for it.
Condition-specific notes
- Tennis and golfer's elbow
- Rotator cuff tendinopathy
- Frozen shoulder, where radial ESWT added to physical therapy has direct randomized adhesive-capsulitis evidence (evidence review)
- Plantar fasciitis and persistent plantar heel pain
- Selected persistent posterior tibial tendon pain. Radial ESWT has preliminary direct evidence in persistent tibialis posterior tendinopathy, although the current condition-specific evidence is limited (evidence review)
- Selected peroneal tendinopathy. Peroneal tendinopathy may be treated with ESWT in selected cases, although condition-specific evidence remains limited (evidence review)
- Selected persistent tibialis anterior tendinopathy. Tibialis anterior tendinopathy may be treated with ESWT in selected persistent cases, although condition-specific evidence remains limited (evidence review)
- Selected chronic calf muscle injury. Radial pressure-wave therapy has demonstrated antifibrotic effects in experimental skeletal-muscle models and has been studied clinically in muscle injury, although protocols remain less standardized than tendon protocols (evidence review)
- Selected chronic adductor-related or muscular groin presentations, after the pain source has been localized (adductor and groin pain). Radial-specific groin trials are limited (evidence review)
- Selected persistent iliopsoas tendon pain, although direct condition-specific comparative evidence remains limited and no study has shown radial shockwave to be better for this deep tendon (evidence review)
- Selected persistent skeletal-muscle injuries, including some chronic quadriceps presentations. Direct rectus-femoris-specific trials are limited (evidence review)
- Selected chronic distal biceps tendinopathy. Chronic distal biceps tendinopathy has direct radial-ESWT clinical evidence. In a 48-patient case-control study, pain outcomes remained significantly better than comparison care through 12 months (evidence review). It is not used for a complete rupture or a significant partial tear
- Selected chronic muscle-tendon injuries of the pectoralis major, after a significant tear has been excluded. Direct pectoralis-specific trials are lacking, so this relies on broader muscle-injury evidence (evidence review)
- Selected persistent distal-triceps tendinopathy, after a significant tear and olecranon bursitis have been excluded. Condition-specific comparative evidence remains limited (evidence review)
- Selected superficial muscular or myofascial chest-wall conditions, on appropriate targets away from the lungs and heart and after fracture, slipping rib and medical causes have been excluded. Direct intercostal-specific evidence is limited (rib and intercostal pain, evidence review)
- Selected superficial abdominal-wall muscle or myofascial conditions, on targets over bone or superficial muscle and never directed toward the abdominal organs, after hernia, nerve entrapment and visceral causes have been excluded. Direct abdominal-wall-specific evidence is limited (abdominal wall pain; evidence review).
- Selected painful temporomandibular disorders with a muscular component. A randomized 80-patient trial used radial shockwave and reported better pain, mouth-opening and jaw-function scores than ultrashort-wave therapy; the placebo-controlled myogenous TMD trials used focused shockwave, and neither modality has been shown to be superior (evidence review).
- Selected moderate trigger finger. Radial ESWT has emerging direct comparative evidence for moderate trigger finger: a 2026 prospective study of 42 patients found that both radial ESWT and corticosteroid injection improved, with faster early relief after injection and better six-month results after radial ESWT. Allocation was non-randomized, so this is supportive rather than definitive evidence, and the randomized trigger-finger trials used wide-focused or unspecified devices (evidence review)
- Selected mild-to-moderate carpal tunnel syndrome. Radial ESWT has direct randomized evidence in carpal tunnel syndrome, including a double-blind sham-controlled trial and a 2026 trial in which adding six weekly radial sessions to conservative care improved symptoms, pain and several nerve-conduction measures. Focused ESWT has also been studied, neither has been shown to be superior, and shockwave does not decompress the nerve (evidence review)
- Achilles tendinopathy. Low-energy radial shockwave is the modality used in several classic randomized Achilles tendinopathy trials. Outcomes differ between insertional and midportion disease, so Achilles treatment is selected by presentation rather than diagnosis alone
- Patellar tendinopathy. Radial ESWT has been studied in chronic patellar tendinopathy, with the newest patellar-specific meta-analysis showing substantial average improvement in pain and VISA function, although results still depend on population, loading strategy and comparator (evidence review)
- Proximal hamstring tendinopathy. ESWT has randomized clinical evidence in chronic proximal hamstring tendinopathy, including a 2025 trial in which shockwave and individualized physiotherapy produced similar outcomes (evidence review)
- Chronic low back pain, when the exam points to the paraspinal muscles and thoracolumbar fascia region
- Neck pain and tension headaches, when the exam points to upper-trapezius myofascial pain
- Lateral hip pain and gluteal tendinopathy, where radial ESWT also has randomized evidence in greater trochanteric pain syndrome
- Selected deep-gluteal and piriformis presentations of sciatic nerve pain. Radial ESWT has randomized clinical evidence in piriformis syndrome, with outcomes similar to corticosteroid injection in one trial (evidence review)
- Fibrous muscle adhesion in fascia and muscle bellies
Precautions
When We May Not Use It
We screen for these at your exam. Any of them can rule radial shockwave out or change the plan:
- Pregnancy
- Blood thinners or a bleeding disorder
- Cancer in the treatment area
- A recent steroid (cortisone) injection into the area
- Infection or broken skin in the treatment area
- Open growth plates in the treatment area
- On the chest or abdominal wall, any target that would direct energy toward the lungs, heart or abdominal organs
Another approach comes first when:
- a tendon rupture or significant tear is suspected
- a fracture or stress fracture is possible
- numbness, tingling or weakness is progressing
- the pain pattern points to a joint, spinal or medical problem that needs imaging or referral
Evidence
What the Evidence Shows
Radial shockwave has been studied in more conditions than many patients expect, but results vary by condition, protocol and comparison treatment.
Most consistent support
Chronic plantar fasciitis: a large multicenter placebo-controlled trial of radial ESWT reported clinically meaningful benefit (Gerdesmeyer, 2008).
Achilles tendinopathy: classic randomized trials used low-energy radial treatment, with better results than eccentric loading in insertional disease and added benefit when combined with loading in midportion disease (Rompe, 2008; Rompe, 2009).
Moderate or mixed evidence
Not every trial is positive. In a 200-patient plantar heel pain trial in which everyone received advice and custom orthoses, adding radial ESWT gave no additional benefit at six months (Heide, 2024).
A 2026 randomized trial in lateral epicondylitis (Journal of Orthopaedic Science) compared radial ESWT plus exercise with exercise alone. Pain dropped more with the combination at 6 and 12 weeks. Both radial and focused ESWT have tennis elbow evidence, with different strengths by outcome. See shockwave therapy for tennis elbow.
In chronic low back pain, meta-analyses of randomized trials report less pain and disability with shockwave than with comparison treatments, with the strongest 2026 results when it was combined with physical therapy. See shockwave therapy for chronic low back pain for the trials and their limits.
Emerging or limited evidence
Added to standard rehab, radial ESWT has improved pain and motion in fibrosis after back surgery. Carpal tunnel syndrome, trigger finger, distal biceps tendinopathy and chronic muscle injury have small, non-randomized or largely experimental evidence, noted condition by condition above.
A 2026 randomized trial in 60 adults with degenerative rotator cuff tendinopathy and partial-thickness supraspinatus tearing (Wang et al., Journal of Clinical Medicine) found greater short-term improvement with radial ESWT plus home exercise than with a program of passive physical-therapy modalities (interferential current, shortwave diathermy, and magnetothermal therapy) plus the same home exercise. The trial did not compare ESWT with progressive exercise-based rehabilitation. See shockwave therapy for rotator cuff tendinopathy for the trial's limits.
Sources: Gerdesmeyer et al., Am J Sports Med 2008 · Rompe et al., J Bone Joint Surg Am 2008 · Rompe et al., Am J Sports Med 2009 · Heide et al., Br J Sports Med 2024 · Tan & Güngör, Journal of Orthopaedic Science, 2026 · Wang et al., Journal of Clinical Medicine, 2026
What to expect
What Treatment Feels Like
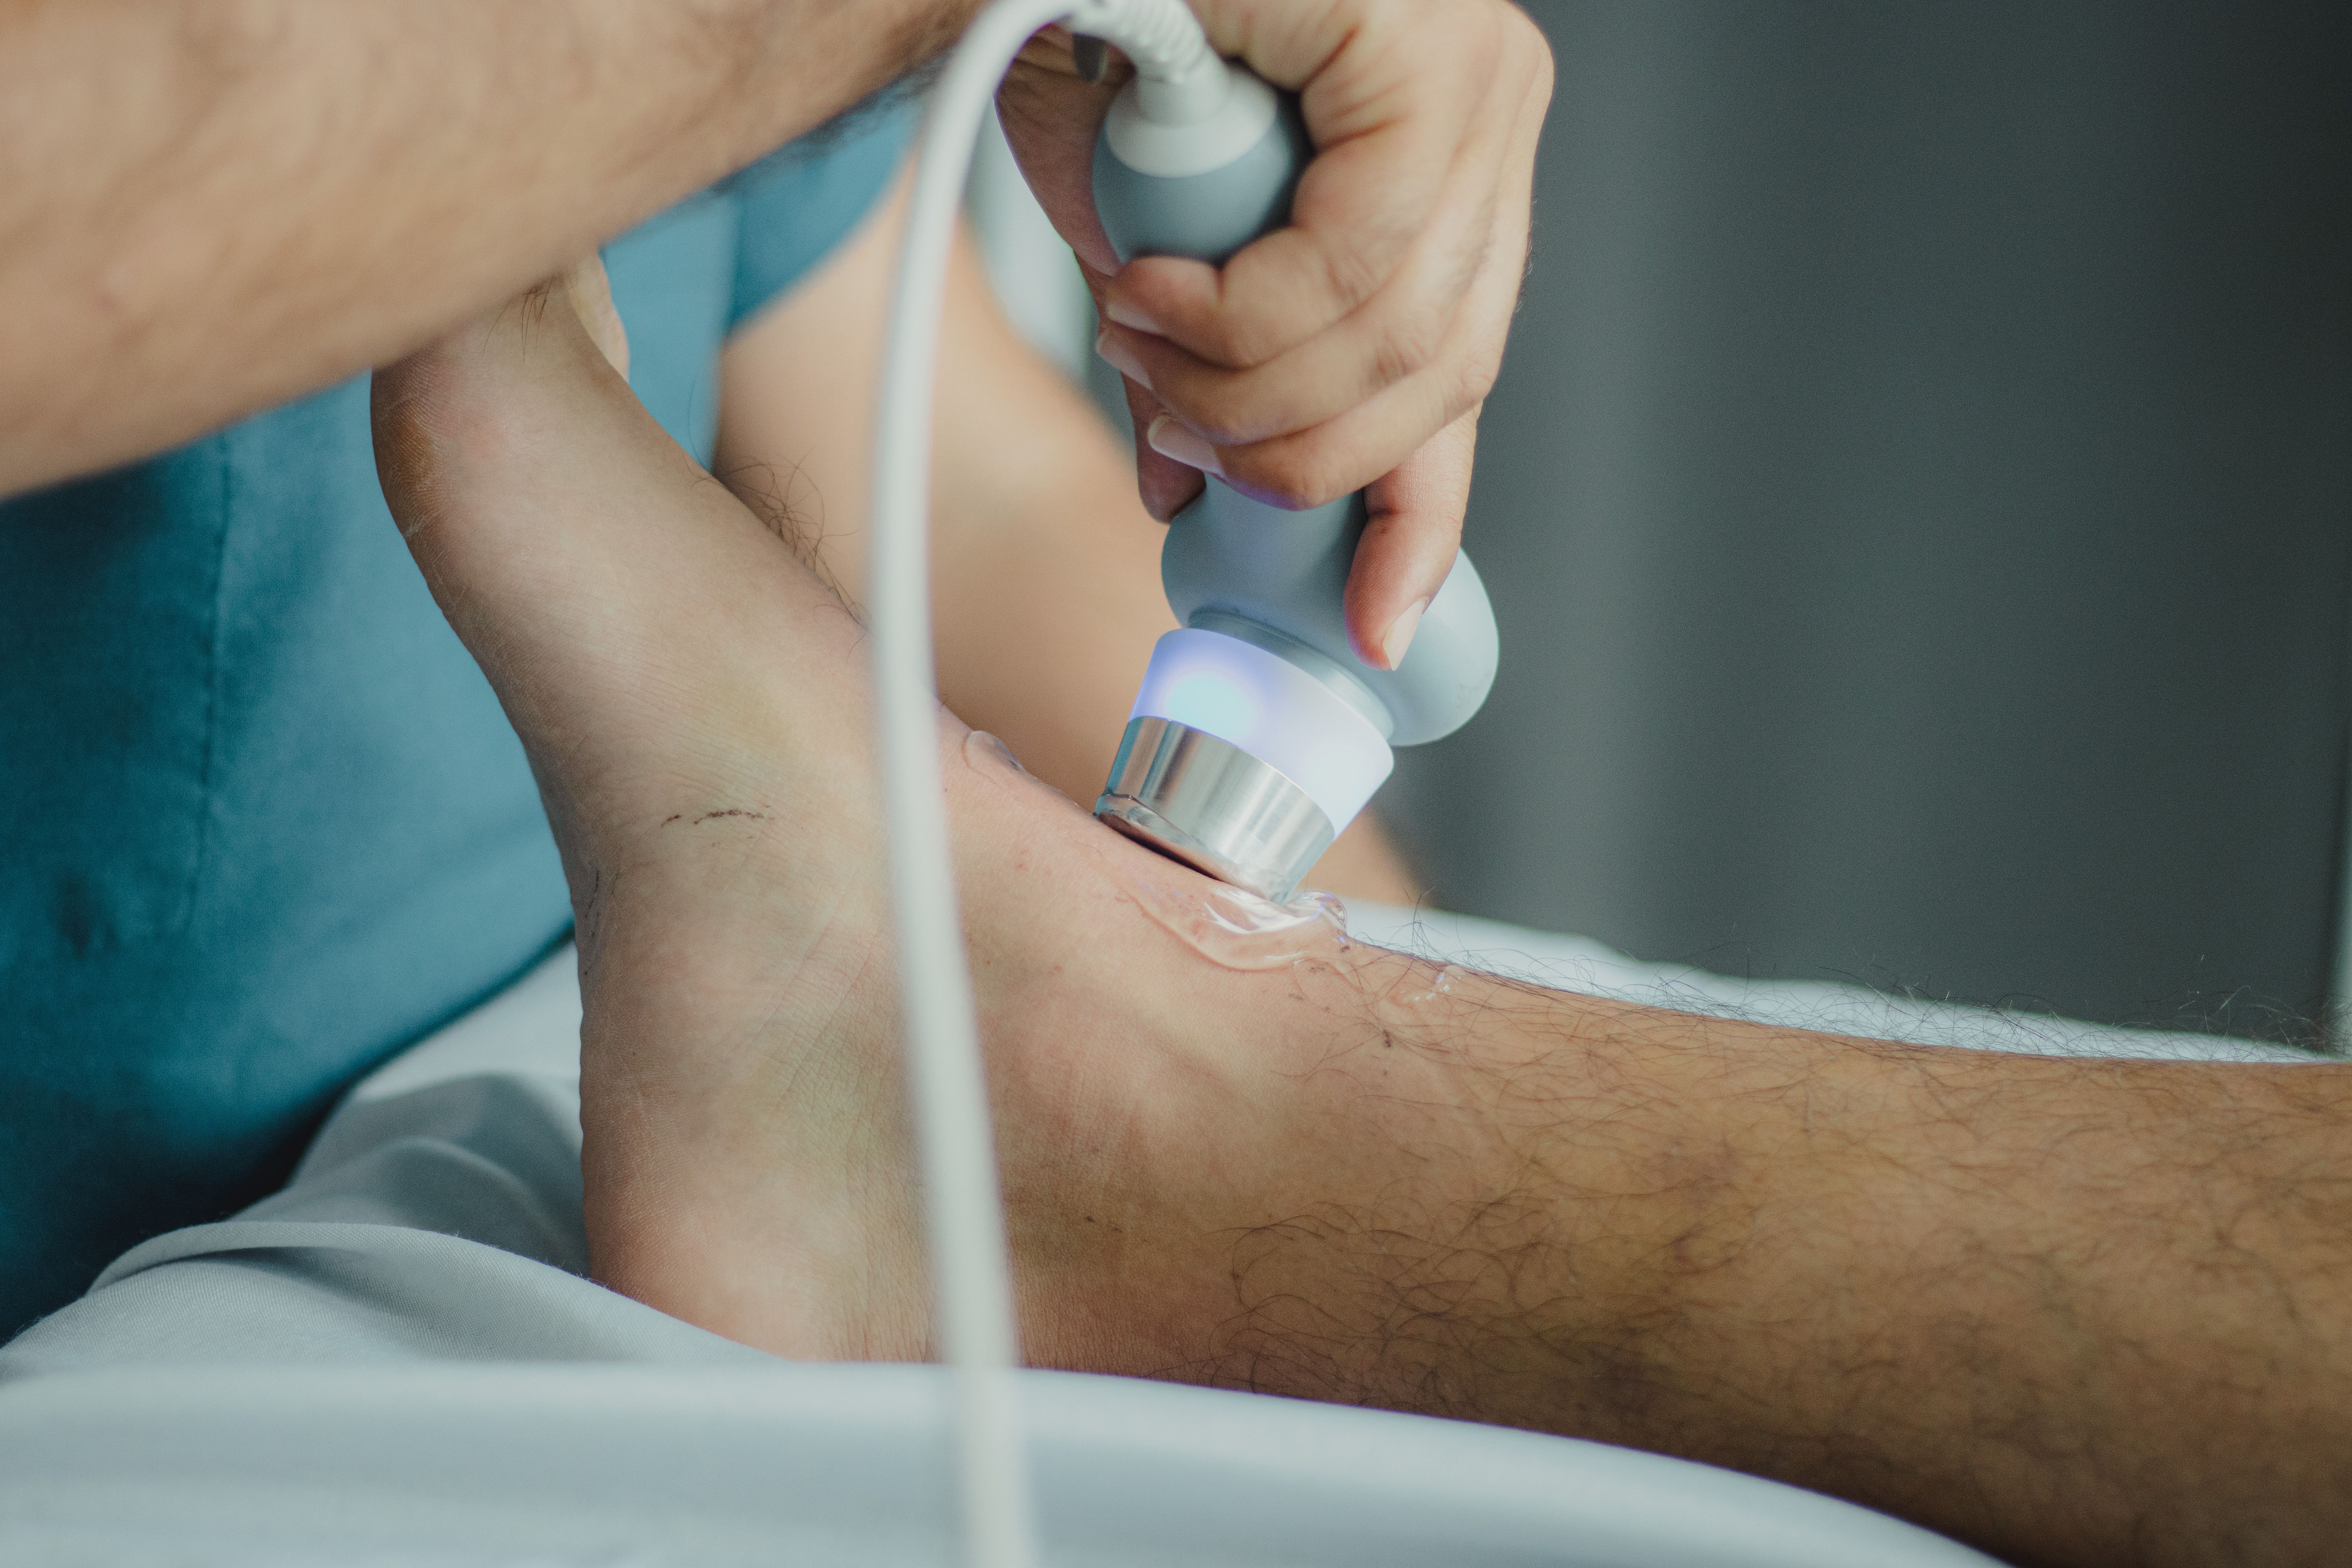
- It is usually part of a 10–15 minute follow-up visit.
- We adjust the intensity to you. It can sting over a tender spot.
- Avoid ibuprofen and other anti-inflammatories for a few days afterward.
- We re-measure range of motion and strength at most visits to track change.
Usually 4–6 sessions, one week apart. The exact number depends on your diagnosis. It is often combined with manual adhesion release in the same visit.
Treatment selection
How Novo Decides Whether to Use It
Radial shockwave is not selected in advance. We first determine which tissue appears to be contributing to the problem and whether it is broad and superficial or small and deep. Each tool has a different role:
- Focused shockwave: a small or deep target, such as a tendon insertion or calcific deposit.
- Radial shockwave: a broader, more superficial area of muscle, fascia or tendon.
- EMTT: a joint or a deeper, broader tissue volume where a mechanical pulse may not suit.
- Manual treatment: restricted muscle or fascia found by hand.
- Load modification and exercise: part of most tendon and muscle care, with or without a device.
- Imaging or referral: when the exam points to a tear, fracture, nerve compromise or a medical cause.
Some problems need one of these, some need a combination, and some need none of them. You do not need to choose a treatment before your visit.